
Plantar fasciitis that has not resolved after months usually comes down to one of three things. The treatment has not been consistent enough or given long enough. The diagnosis is wrong and something else is causing the heel pain. Or the fascia has a partial tear, which does not respond to the same treatment.
Roughly nine in ten cases settle with non-surgical treatment, but the honest part of that statistic is the timeline: it commonly takes six to twelve months, and people give up at week six. Before assuming you are the exception, it is sensible to work out which of the three you are actually dealing with.
Reason one: it has not had a fair trial
The treatments that work for plantar fasciitis are unglamorous and they work by accumulation rather than by breakthrough. Done properly and daily, most people improve. Done for two weeks and abandoned, almost nobody does.
A fair trial means all of the following, together, for at least three months.
- Calf and plantar fascia stretching every day, including before the first steps in the morning. Tight calves are one of the strongest drivers of this condition and are frequently the thing that has not been addressed.
- Supportive shoes at all times, including indoors. Barefoot on hard floors at home undoes a great deal of daytime progress.
- Arch support, either over-the-counter or custom, depending on your foot.
- Reducing the aggravating load rather than stopping activity altogether.
- Ice after activity, and anti-inflammatory medication if your physician says it is appropriate for you.
- A night splint if morning pain is the dominant symptom. This is the treatment people most often skip and it is one of the more effective ones.
If you have not done all of that consistently, the first step is not a more aggressive treatment. It is doing this properly for three months.
Reason two: it may not be plantar fasciitis
Heel pain has several causes and they get treated as one. If months of correct plantar fasciitis treatment have produced nothing at all, that is itself diagnostic information.
What gets mistaken for plantar fasciitis
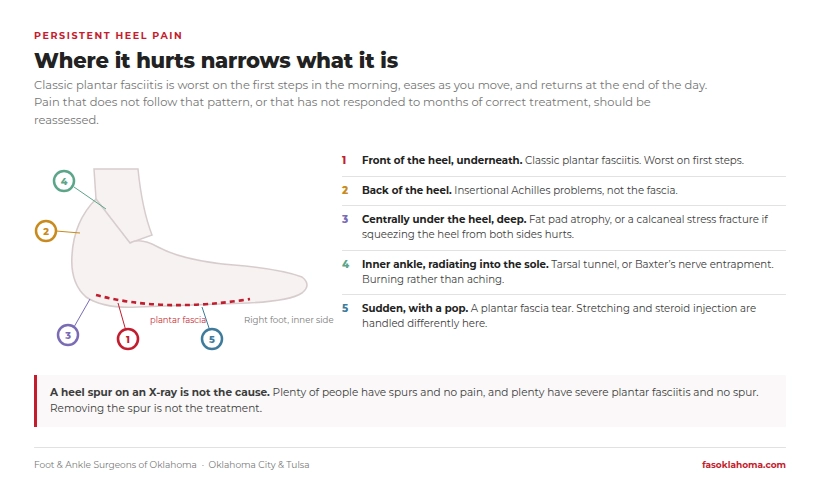
- A calcaneal stress fracture. Pain that is present at rest and when squeezing the heel from both sides, rather than worst on first steps, points here. This is a common miss and continuing to exercise on it makes it worse.
- Baxter’s nerve entrapment. Burning, tingling, or pain that radiates rather than staying in one spot under the heel.
- Tarsal tunnel syndrome, which produces numbness or burning across the sole.
- Fat pad atrophy, where the natural cushion under the heel has thinned. The pain sits centrally under the heel rather than at the front of it, and it is common with age.
- Achilles or insertional tendon problems, where the pain is at the back of the heel rather than underneath it.
- Inflammatory arthritis. Bilateral heel pain in a younger patient, or heel pain alongside back or joint symptoms elsewhere, deserves a broader look.
- A referred problem from the lower back.
Classic plantar fasciitis hurts most with the first steps in the morning or after sitting, eases as you move, and returns at the end of the day. Pain that does not follow that pattern should be reassessed.
Reason three: the fascia may be torn
A partial tear of the plantar fascia is different from the degenerative, overloaded fascia that most people have. It often starts suddenly, sometimes with a pop or a distinct moment, and it tends to be more painful with sharper, more localised pain.
Tears do not respond well to stretching, and a steroid injection into a torn fascia is generally avoided because it can weaken the tissue further. Distinguishing this changes the whole treatment plan, and it usually needs imaging rather than examination alone.
How the diagnosis is actually confirmed
Most plantar fasciitis is diagnosed clinically, from the history and an examination that reproduces the pain at the point where the fascia attaches to the heel bone. That is sufficient in a straightforward case.
When a case is not resolving, imaging earns its place. Ultrasound shows the thickness of the fascia and identifies tears. An X-ray rules out a stress fracture and shows the bone. MRI is reserved for cases where the picture is still unclear or a nerve problem is suspected.
A heel spur on an X-ray, incidentally, is not the cause of the pain. Plenty of people have spurs and no symptoms, and plenty have severe plantar fasciitis and no spur. Removing a spur is not the treatment.
Treatments beyond the basics
Corticosteroid injection
Effective for short-term pain relief in many people and useful for breaking a cycle where pain is preventing the stretching that would help. The relief is often temporary, repeated injections carry a risk of fascia rupture and fat pad thinning, and it is generally avoided where a tear is suspected.
Extracorporeal shockwave therapy
Delivers acoustic waves to the tissue to stimulate a healing response. It is a reasonable option for cases that have failed several months of conservative treatment and it avoids the risks of injection. Coverage by insurance is inconsistent, so check before you commit.
Radiofrequency treatments, including Topaz
A minimally invasive technique that makes small channels in the fascia to prompt a healing response. It is used for chronic cases and sits between conservative treatment and open surgery in how invasive it is. Whether it is the right step depends on the specific findings in your foot.
Platelet-rich plasma and similar injections
Studied for chronic plantar fasciitis with mixed results. Some patients do well. It is generally not covered by insurance, and it is fair to describe the evidence as promising rather than settled.
When surgery enters the conversation
Surgery is considered after at least six to twelve months of genuine, consistent non-surgical treatment has failed, and once the diagnosis has been confirmed rather than assumed. It is not a first step and it is not a large proportion of cases.
The usual procedure is a plantar fascia release, in which part of the fascia is divided to reduce tension at its attachment. It can be done open or endoscopically. Where a nerve entrapment is contributing, that may be addressed at the same time.
What recovery involves
Recovery generally runs three to ten weeks depending on the technique, with endoscopic release recovering faster than open surgery. Expect a period in a walking boot or surgical shoe, a gradual return to weight-bearing, and physical therapy to restore movement. Return to running or high-impact activity typically waits at least eight to twelve weeks and often longer.
The trade-off is real and you should know about it before you consent. Releasing the fascia reduces tension, and the fascia is part of what supports the arch. A minority of patients develop arch discomfort or pain elsewhere in the foot afterwards. This is why the operation is reserved for people who have exhausted the alternatives.
What to do next if you are stuck
If you have been treating this correctly for three months and nothing has changed, the useful next step is a reassessment rather than another month of the same. The question to have answered is whether this is actually plantar fasciitis, and whether the fascia is intact.
Our heel pain and plantar fasciitis page covers how we work through that.
Common questions about plantar fasciitis that will not resolve
How long should plantar fasciitis take to go away?
Most cases resolve with consistent non-surgical treatment, commonly over six to twelve months. Improvement is gradual rather than sudden, which is why people underestimate their own progress and stop too early.
What are the signs plantar fasciitis is healing?
The morning pain arrives less sharply and eases faster. You can walk further before symptoms start. End-of-day pain is less intense. Progress in this condition shows up as a shrinking bad patch rather than a good day.
What gets mistaken for plantar fasciitis?
Calcaneal stress fractures, Baxter’s nerve entrapment, tarsal tunnel syndrome, fat pad atrophy, insertional Achilles problems, and inflammatory arthritis. If months of correct treatment have changed nothing, the diagnosis is the first thing to revisit.
Why do I have plantar fasciitis in only one foot?
Usually because that foot is loaded differently, through a mechanical difference, an old injury, a leg length difference, or a change in gait. Pain in both heels at once, particularly in a younger person, raises the possibility of an inflammatory cause and deserves a broader assessment.
Is it worth getting plantar fasciitis surgery?
For the small group who have exhausted six to twelve months of proper conservative treatment with a confirmed diagnosis, many do well. It is not a reasonable option before that, both because most people improve without it and because the release carries a genuine trade-off in arch support.
What is the worst thing you can do for plantar fasciitis?
Walking barefoot on hard floors, particularly first thing in the morning. After that, stopping treatment as soon as it starts helping, and pushing through increasing pain rather than reducing the load that is causing it.
Does a heel spur cause plantar fasciitis?
No. Spurs are common in people with no heel pain and absent in many people with severe symptoms. The spur is a consequence of long-term traction rather than the source of the pain, and removing it is not the treatment.
Get it looked at properly
Heel pain that has lasted months is worth a proper diagnosis rather than another round of guessing. That is one appointment, an examination, and imaging if it is warranted.
Our surgeons see patients in Oklahoma City and Tulsa, with clinics across Oklahoma. Request an appointment or call the office closest to you.